Use of the coronary artery calcium (CAC) score in people with intermediate risk of cardiovascular disease as well as a family history of cardiac problems can help improve outcomes in this group.
As reported in JAMA Cardiology, using this scoring system to assess risk combined with preventative lifestyle change in those with high scores reduced signs of atherosclerosis and improved the health of participants.
Heart disease is the leading cause of death in adults in the United States, with one person dying every 33 seconds from cardiovascular disease. Healthcare costs associated with cardiovascular disease are also extremely high at over $250 billion per year.
For many types of heart disease, intervention in the early stages of disease can be lifesaving and various screening tests and diagnostic tools exist to try and detect who is at greatest risk and in need of early intervention. One such tool is the CAC score, which uses coronary computed tomography angiography imaging to calculate a person’s risk of having a more serious cardiac event such as a heart attack.
“To date, observational evidence indicates that the CAC score can be used to reclassify risk, with most incident events occurring in participants with CAC scores of 100 or greater,” wrote lead author Thomas Marwick, PhD, professor, Baker Heart and Diabetes Institute, Melbourne, and colleagues.
Around 50% of people are classified as intermediate risk of developing cardiovascular disease according to factors such as smoking, high blood pressure, having diabetes, and having high levels of lipids such as low-density lipoprotein cholesterol, as well as having a family history of heart disease.
“Although a family history of premature coronary artery disease can provoke treatment at lower thresholds, standard pharmacological or lifestyle interventions show only modest returns in the intermediate-risk group,” wrote the authors.
To investigate if use of the CAC score in people at intermediate risk with a family history could improve outcomes, Marwick and colleagues recruited 365 people aged 40–70 years to take part in the study. Approximately half the group had preventive advice and/or treatment for symptoms based on the CAC score and the other half had usual care and acted as controls.
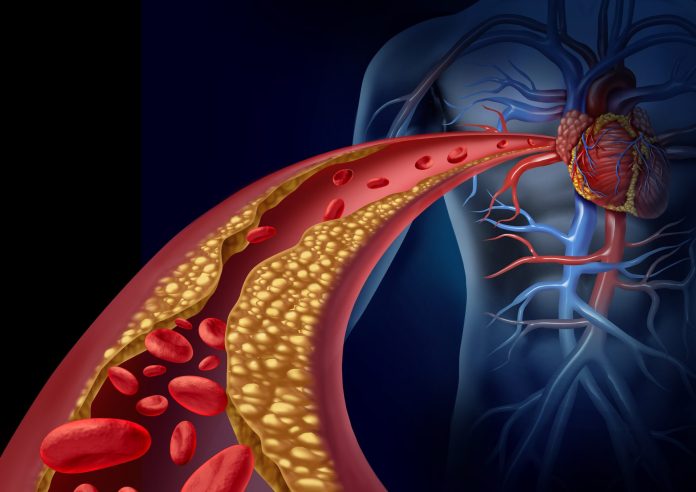
After three years follow-up, the results showed that at-risk individuals who were in the CAC score guided group showed reductions in bad cholesterol and a slower progression of atherosclerosis plaque build up in their blood vessels compared with controls.
“These results may support the use of the CAC score to inform the use of more intensive preventive strategies in intermediate-risk patients,” concluded the research team, although they caution that the results are open-label and should be validated.